Gynaecological tests and procedures
HPV PCR and genotyping in our own laboratory
Molecular detection of human papillomavirus DNA, with identification of risk genotypes and a result usually available on the same day when the sample reaches the laboratory in suitable condition and within the operational workflow.

Explained in clear language
What it is
This is a molecular laboratory analysis performed on a cervical or vaginal sample. It detects HPV genetic material and helps assess risk and plan follow-up. It does not by itself diagnose cancer or a precancerous lesion. Depending on the indication, the same technology may be used for screening, triage, diagnostic assessment or follow-up.

How it is performed
- 1
Individual assessment and indication
- 2
Explanation, alternatives and consent
- 3
Procedure with appropriate safeguards
- 4
Results, aftercare and follow-up
Askabide visual archive
The procedure, also explained through images
The photographs come from Askabide’s clinical and “more information” sections. They have been selected by clinical area to support the explanation; not every image is a literal representation of each manoeuvre and none replaces an individual medical explanation.
Assessment and indication
The indication is decided after listening to the reason for attending, reviewing history and explaining the clinical question that needs to be answered.
How it is carried out
The technique, sample collection, device or intervention is adapted to the individual situation and explained before it starts.
Results and follow-up
The result is not interpreted in isolation: symptoms, examination, age, history and complementary tests are considered together.
Clinical detail
Enlarged images help explain the setting and stages of care, but final planning is always individualised.
Askabide Laborategia
How Askabide performs HPV PCR
Own laboratory · result usually available the same dayThe test does not simply “look” for the virus: the laboratory extracts and amplifies genetic material to detect HPV and, depending on the panel, report genotypes or risk groups.
- A cervical or vaginal sample is collected with a dedicated brush, usually during a speculum examination.
- The sample is identified, preserved and transported through the pre-analytical pathway.
- Genetic material is extracted and amplified by PCR with internal controls that verify the validity of the reaction.
- The result and genotype information are reported and interpreted with cytology, medical history and examination findings.
Same-day turnaround depends on reception time, sample quality and internal controls. An insufficient sample, invalid control or need to repeat amplification can extend the reporting time.

VPH / HPV
How HPV types are classified
Low risk
Types 6 and 11 are most strongly associated with genital warts. They are considered low oncogenic risk: they can cause visible lesions but are rarely linked to cancer.
High risk
The recognised high-risk types are 16, 18, 31, 33, 35, 39, 45, 51, 52, 56, 58 and 59. Persistence, rather than a single positive result, is the factor that may lead to precancerous cellular changes.
Types 16 and 18
These genotypes make the largest contribution to HPV-related cancers. A positive result requires more precise risk assessment, but still does not mean that cancer is present.
Other genotypes and co-infection
More than one genotype may be detected. Management depends on type, age, cytology, persistence, immune status, history and current clinical guidance.
What the result may mean
No genetic material included in the panel is detected in that sample. The follow-up interval depends on age and the reason for testing.
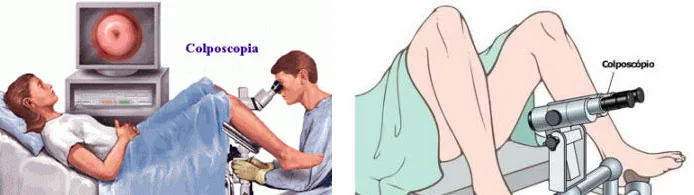
This is not the same as cancer. It usually requires closer risk assessment and follow-up, with cytology or colposcopy according to context.
This is interpreted with cytology, history and persistence. Follow-up, cytology triage or colposcopy may be recommended.
This must not be interpreted as negative. The internal control is reviewed and the sample or analysis may need to be repeated.
This is a molecular laboratory analysis performed on a cervical or vaginal sample. It detects HPV genetic material and helps assess risk and plan follow-up. It does not by itself diagnose cancer or a precancerous lesion. Depending on the indication, the same technology may be used for screening, triage, diagnostic assessment or follow-up.
What PCR actually detects
PCR detects HPV DNA in the analysed sample. It may identify specific genotypes or high-risk groups. It is a laboratory diagnostic test for the presence of virus in that sample; on its own it does not confirm a lesion or predict whether the infection will persist.
When it may be indicated
It may be used after abnormal cytology, to complete cervical assessment, to monitor persistent infection or a treated lesion and, depending on age and programme, as a primary screening test. Testing should not be driven by anxiety alone.
Sample collection and preparation
A brush is usually used to collect a sample from the cervix or vagina. Tell the team about bleeding, pregnancy, recent vaginal treatment or previous cervical procedures. The appointment may be rescheduled to improve sample quality.
Combined interpretation
The result is combined with age, cytology, colposcopy, biopsy, history and persistence. HPV may be detected years after acquisition or reactivate; the result cannot date the infection or attribute it to a particular partner.
Treatment and monitoring
There is no recommended antibiotic or antiviral treatment to eradicate subclinical HPV infection. Many infections are controlled spontaneously. Treatment is directed at manifestations such as warts, precancerous lesions or cancer, while persistence is monitored according to risk.
Prevention
Vaccination reduces risk from the genotypes covered by the vaccine. Condoms reduce transmission but do not eliminate it because uncovered skin may still have contact. Vaccination and condoms do not replace recommended cervical follow-up.
What should not be concluded
A positive result does not mean cancer, infidelity or recent infection. A negative result does not replace assessment when there are visible lesions, abnormal bleeding or persistent symptoms. Not all HPV causes warts and not all wart-causing types are high risk.
Follow-up plan
The plan may include cytology, colposcopy, targeted biopsy, repeat HPV testing or return to the recommended interval. Follow-up is matched to risk to avoid both loss to follow-up and unnecessary procedures.
Related procedures


Askabide Klinika
Not sure which procedure you need?
You do not need to choose a test on your own. Tell us what concerns you and the team will guide you after assessing your situation.